

Healthy growth during adolescence represents one of the most dynamic and sensitive phases of human development. For many families, questions arise when a child’s height appears below expectations or when their growth does not align with family patterns. At HGH Vallarta Clinic, our role as pediatric endocrinologists is to carefully evaluate growth, determine underlying causes, and create treatment strategies to support each child’s unique potential. Using detailed clinical information, including height percentiles, bone age, IGF‑1 levels, and metabolic markers, allows us to provide evidence‑based guidance on whether growth hormone therapy may be beneficial.
The medical reports reviewed in this case provide a clear example of how clinical decisions are formed. Leon R., a 15‑year‑old adolescent, presented with normal endocrine lab results, normal growth velocity, and normal growth hormone production. However, his height remained below his familial target height, suggesting potential benefit from height‑optimization therapy. Understanding the implications of these findings helps parents make informed decisions about treatment options.
Understanding Height Expectations and Genetic Potential
A child’s final adult height is influenced strongly by genetics. Pediatric endocrinologists calculate “mid-parental height” or familial target height, to determine where a child should naturally fall on the growth curve. When a child’s height percentile is significantly lower than their genetic expectation, the circumstance may indicate a growth pattern that warrants intervention, even when lab values appear normal.
In Leon’s case, his height percentiles ranged from the 27th to the 56th percentile across different evaluations, but his projected genetic target height ranged from 181.7 cm to 185.31 cm. This difference suggests that while his height is appropriate for the general population, it may not align with genetic expectations. This clinical discrepancy is one of the main reasons to consider growth hormone therapy for height optimization.
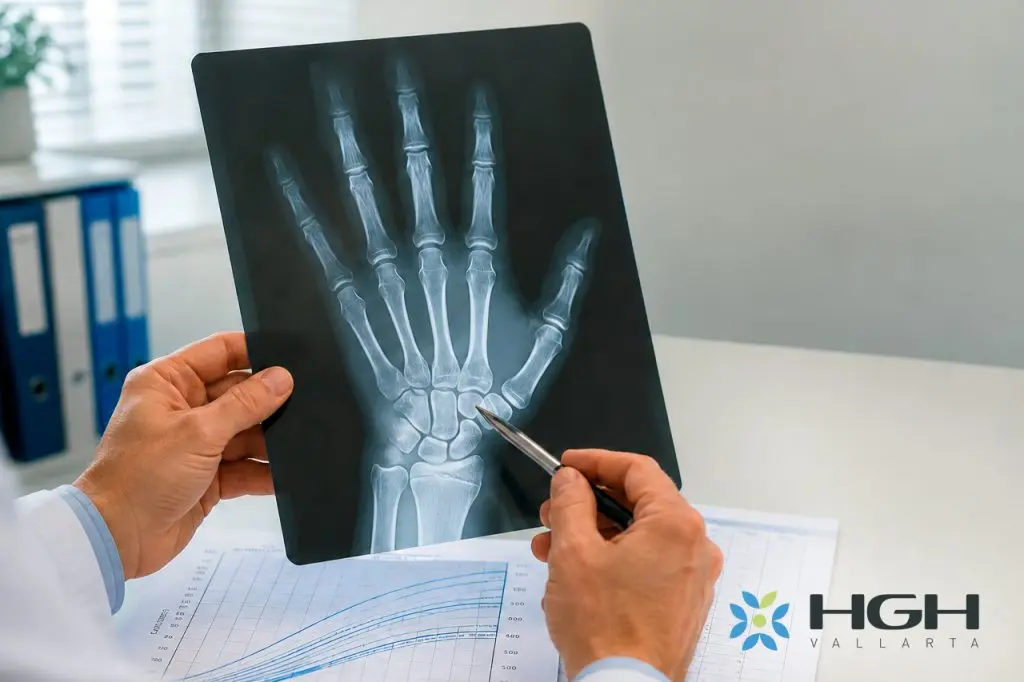
Evaluating Growth Velocity and Bone Age
Growth velocity, the rate at which a child grows each year, is a critical indicator of whether the child is progressing normally. Leon’s growth velocity of approximately 5.2 cm per year is consistent with normal adolescent growth. However, the relationship between growth velocity and remaining growth potential depends heavily on bone age.
Bone age reflects the maturity of the skeleton and helps estimate how much time remains before growth plates close. Leon’s bone age was consistent with his chronological age, suggesting that he is in mid‑puberty and still has growth potential remaining. However, because bone age was not delayed, the window for maximizing height is narrower than it would be in a younger or less mature adolescent.
Laboratory Markers: IGF‑1, Thyroid Function, and Metabolic Health
IGF‑1 (Insulin‑Like Growth Factor 1) is a key indicator of growth hormone activity. Leon’s IGF‑1 levels, measured at 433 ng/ml in one report and 773 ng/ml in another, were within normal range. This indicates that his body is already producing an adequate amount of growth hormone. As a result, Leon is not growth hormone deficient. However, therapeutic growth hormone may still be used to optimize final height when appropriate.
Thyroid function in both reports was normal, ruling out hypothyroidism, a common cause of slowed growth. His HbA1c levels (5.6–5.7%) were at the high end of the typical spectrum, which is important because growth hormone therapy can elevate blood sugar. For this reason, careful metabolic monitoring is essential while on treatment.
The Role of Growth Hormone Therapy in Height Optimization
Growth hormone therapy (somatropin) is not limited to treating growth hormone deficiency. It is often used for adolescents who have normal hormone production but whose height is significantly below their familial target. When started at the right time, GH therapy can speed up growth and add a few centimeters to final adult height.
In Leon’s case, Somatropin doses of 3.5–3.8 mg nightly were recommended. These doses are consistent with weight‑based standards and aim to stimulate growth within a safe therapeutic range. Treatment requires consistent monitoring of IGF‑1 levels, thyroid function, metabolic markers, and periodic bone age imaging.
It is important to recognize that growth hormone therapy is most effective when bone plates remain open. Because Leon’s bone age is progressing normally, the potential height gain is moderate but still meaningful. Therapy decisions depend on family goals, medical safety, and remaining growth potential.
Aromatase Inhibitors: Why They Were Not Recommended
Aromatase inhibitors are sometimes used in boys to delay bone maturation and extend the growth window. However, these medications carry risks, and their use must be carefully evaluated. In Leon’s case, aromatase inhibitors were inadvisable because his bone age indicated sufficient advancement and no clinical need. Early or unnecessary use could pose risks without substantial benefit.
The Importance of Weight and Metabolic Health
Leon’s BMI was in the high‑normal to overweight range. Higher BMI can blunt growth hormone sensitivity and increase the risk of insulin resistance. For this reason, lifestyle modifications, including nutrition guidance and physical activity, were part of his overall care recommendations. Weight management supports safer and more effective growth hormone therapy.
Follow-Up and Long-Term Monitoring
Effective hormone treatment requires careful, ongoing follow‑up. At HGH Vallarta Clinic, we typically reassess patients every three to six months with updated labs, dose adjustments, and imaging as needed. Regular monitoring reduces risks and ensures that therapy remains safe and productive.
Final Thoughts for Parents
Every child’s growth journey is unique. While many adolescents grow normally without intervention, others may benefit from specialized evaluation and treatment to reach their full height potential. Decisions regarding growth hormone therapy should always be individualized and made in partnership with a pediatric endocrinologist who understands the nuances of growth patterns, bone maturation, and long‑term safety.
Growth optimization is about more than achieving a target number; it’s about ensuring a healthy transition to adulthood with confidence, physical well‑being, and supportive medical care.

Understanding Your Child’s Growth
Many parents wonder whether their child is growing normally or whether they might need medical help to reach their full height potential. This summary explains the key ideas in simple terms.
Every child develops at their own pace, but genetics significantly influence final height. Doctors compare your child’s current height to the expected range based on their parents. If your child is much shorter than this range, growth hormone therapy may be beneficial, even if lab results appear normal.
In Leon’s case, he is growing normally for his age, but his height is still below what we would expect given his family’s height. This means treatment can be an option to help him approach his natural potential.
Growth hormone treatment uses a medication called Somatropin, taken daily at night. It is safe when monitored closely and can help increase final height. Doctors track progress through blood tests, bone age X-rays, and regular check-ups.
Some children also need assistance with weight because being overweight can impact growth and hormone levels. Lifestyle choices, proper nutrition, sleep, and physical activity also play important roles.
If you’re noticing differences in your child’s height, growth pace, or development, or if you simply want clarity about whether they are reaching their genetic potential, our team at HGH Vallarta Clinic is here to help.
We provide comprehensive growth evaluations, bone age studies, expert endocrine analysis, and personalized treatment plans designed to support healthy, confident development.
Schedule a consultation with our pediatric endocrinology team today.









